
Bladder Outflow Blockage (BOO) & Urinary Retention: Fast Diagnosis & Evidence-Based Relief
Urinary hesitancy, severe straining, the acute agony of being unable to pass urine, or silent high-volume retention are mechanical and neuro-functional warnings. Unrelieved outflow obstruction causes detrusor trabeculation, bladder wall thickening, and dangerous backward pressure into the kidneys.
18+ Yrs
Surgical Leadership
12,000+
Urology Surgeries
Daycare MIST
Rezūm, UroLift, iTind
Pathophysiology Insight
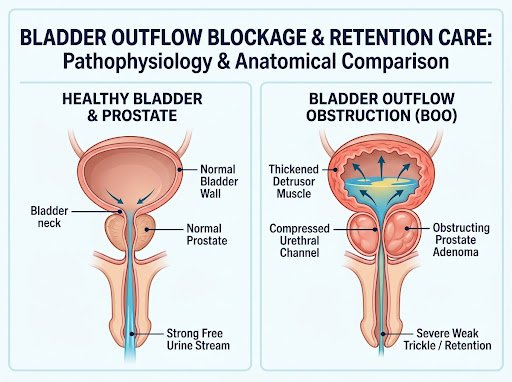
Acute Risk: Unrelieved retention leads to myogenic bladder decompensation, post-renal azotemia, and hydronephrosis.
Prompt Interventions: Atraumatic decompression, laser enucleation (HoLEP), and precise robotic reconstructive release.
Acute vs. Chronic Urinary Retention
Recognizing whether retention is an emergency crisis (AUR) or an insidious, silent failure (CUR) determines immediate clinical preservation protocols.
Acute Urinary Retention (AUR)
A sudden and agonizing inability to pass any urine despite having a tensely filled, painfully palpable bladder. Represents an immediate medical crisis.
Severe Lower Abdominal Pain & Diaphoresis
Patient experiences extreme distress, sweating, tachycardic agitation, and unyielding urge to urinate without output.
Immediate Bladder Rupture & AKI Risk
Sustained intravesical pressure causes detrusor ischemic damage, acute kidney injury, and backpressure hydronephrosis within hours.
Immediate Action: Catheter Decompression
Gentle urethral or percutaneous suprapubic decompression must be performed promptly under aseptic clinical guidance.
Chronic Urinary Retention (CUR)
Painless or mild discomfort where the bladder consistently fails to empty, silently harboring high post-void residual volumes (PVR >300 mL to 1,500 mL+).
Overflow Incontinence & Paradoxical Leakage
Patients mistakenly perceive excessive urination or night bedwetting, which is actually passive overflow from a stretched bladder.
Bilateral Hydronephrosis & Uremia Risk
Prolonged high resting bladder pressure forces urine backwards into ureters, elevating serum creatinine and impairing renal filtration.
Action: Comprehensive Urodynamics & Relief
Gradual decompression followed by Video Urodynamic Study (VUDS) to assess myogenic reserve before definitive endoscopic release.
Causes of Bladder Outflow Obstruction (BOO)
Bladder outlet obstruction can arise mechanically along the urethral tract or functionally due to impaired neuro-vesical transmission.
1. Benign Prostatic Hyperplasia (BPH)
Enlargement of the prostatic transitional zone or median lobe ball-valving into the bladder neck is the primary mechanical trigger in men aged 50 and above.
Prevalence: 70%+ Men over 65
2. Urethral Stricture Disease
Fibrotic luminal narrowing secondary to prior catheterization trauma, straddle injuries, pelvic fractures, or chronic urethritis restricting outward flow.
Requires HD Urethroscopy
3. Bladder Neck Sclerosis
Hypertrophic contracture or scar formation at the internal urethral orifice following previous transurethral resection (TURP) or chronic inflammation.
Laser Neck Incision Relieved
4. Impacted Bladder Calculi
Stones formed in the bladder or migrated from the kidneys that suddenly lodge at the internal bladder neck, causing abrupt painful urinary stoppage.
Painless Laser Cystolitholapaxy
5. Neurogenic Detrusor Underactivity
Impaired bladder smooth muscle contractility caused by long-standing diabetic cystopathy, spinal cord compression, Parkinson's disease, or stroke.
VUDS Differentiated
6. Medication-Induced Retention
Use of potent anticholinergics, over-the-counter decongestants (pseudoephedrine), first-generation antihistamines, or post-operative opioid analgesia.
Rapid Pharmacologic Review
5-Step Diagnostic Protocol for Voiding Dysfunction
Eliminating guesswork: our protocol delineates physical mechanical blockage from detrusor underactivity to safeguard renal filtration.
STEP 01
Bedside Examination
Gentle bimanual palpation & percussion of suprapubic distension, external genitalia check, and focused digital rectal examination (DRE).
- Clinical Exam
STEP 02
PVR Ultrasound
Non-invasive real-time sonography measuring post-void residual urine volume and checking for bilateral ureteric dilatation or hydronephrosis.
- Ultrasound KUB
STEP 03
Uroflowmetry
Computerized flow rate analysis mapping Maximum Flow Rate (Qmax), voided volume, and bell-shaped vs. plateau obstructed voiding curves.
- Qmax Mapping
STEP 04
VUDS Study
Video Urodynamics & pressure-flow recordings (pdet@Qmax) to conclusively differentiate outlet blockage from primary detrusor failure.
- Pressure Flow
STEP 04
Digital Cystoscopy
High-definition flexible fiber-optic endoscopy under local gel anaesthesia to directly map strictures, false passages, or bladder neck spurs.
- HD Visualization
Frequently Asked Questions on Bladder Blockage
Clear, reassuring, and evidence-grounded answers to the questions patients ask most frequently.
What is the core clinical difference between acute and chronic urinary retention?
Acute Urinary Retention (AUR) is an agonizing medical emergency: the patient suddenly cannot pass any urine despite a distended, painful bladder. Chronic Urinary Retention (CUR) is painless and insidious: the patient voids small amounts with high residual volume left behind (PVR >300 mL to 1,500 mL), often causing overflow leakage, recurrent infections, and silent kidney damage.
Can unaddressed urinary retention cause irreversible kidney damage?
Yes. Prolonged high resting pressures inside the bladder overcome the anti-reflux mechanisms of the ureterovesical junctions. This causes bilateral hydroureteronephrosis, progressive thinning of the renal cortex, and secondary obstructive renal failure with elevated blood urea and serum creatinine. Timely decompression reverses this risk if treated before permanent parenchymal loss occurs.
If an emergency catheter was placed, how long do I need to keep it before definitive surgery?
A catheter should only stay in place long enough to achieve detrusor rest, normalize renal chemistry, and complete necessary uro-radiological workups (typically 3 to 14 days). Prolonged catheterization increases the risks of severe urinary tract infections, catheter encrustation, and urethral erosion. At Rajshree Apollo, we expedite definitive laser or daycare procedures to minimize catheter dwell time.
What is a Trial Without Catheter (TWOC) and when is it safe to attempt?
A TWOC involves removing the catheter after administering alpha-blocker therapy (like Tamsulosin or Silodosin) for 48 to 72 hours, to assess if spontaneous voiding returns. It is conducted in a controlled hospital setting with a post-void ultrasound scan. If the residual volume remains high or the patient fails to void, definitive obstruction surgery is required.
Can a urethral stricture cause sudden, acute urinary blockage?
Yes. While stricture narrowing often progresses gradually with stream thinning and spraying, mucosal edema from mild infection or attempts at blind catheterization can suddenly close the pinhole lumen completely, triggering acute retention. Such cases should never be forced with rigid standard catheters, but decompressed gently by a urologist with flexible guidewires or a suprapubic catheter.
Don't Endure Bladder Distress or Delayed Voiding
Acute retention requires instant relief. Chronic hesitancy requires expert protection against detrusor failure. Connect with Dr. Chipde's team at Rajshree Apollo Hospitals, Indore.
Visit Dr. Chipde at Rajshree Apollo Hospitals Indore
Conveniently accessible in Vijay Nagar, Indore. Book an express in-clinic consultation or connect on WhatsApp.
Rajshree Apollo Hospitals, Indore
- Practice Address:
Rajshree Apollo Hospitals, Sector-D, Scheme No. 74C, Vijay Nagar, Indore, Madhya Pradesh 452010
- OPD Clinic Hours:
Monday to Saturday: 10:00 AM – 06:00 PM (Sunday by emergency appointment)
- Direct Phone & WhatsApp: