
HoLEP: Complete Laser Enucleation of Obstructive Prostate Adenoma with Lifetime Durability
When the prostate reaches substantial size (>60g, 100g, or over 200g), standard procedures like TURP face severe limits. HoLEP cleanly peels the entire obstructing adenoma along the natural surgical capsule using high-power Holmium laser energy — offering virtually bloodless clearance, zero incisions, rapid catheter removal, and negligible recurrence rate (<1%).
18+ Yrs
Surgical Leadership
12,000+
Urology Surgeries
Daycare MIST
Rezūm, UroLift, iTind
Anatomical Restoration Architecture
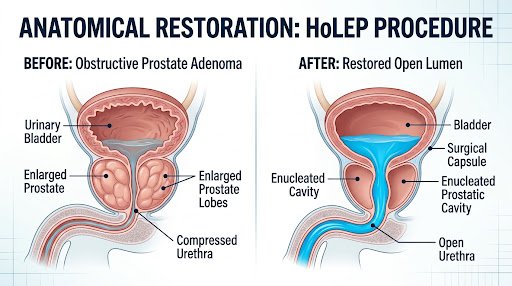
High-power Holmium laser precisely dissects the obstructing adenoma along the anatomical capsule plane, restoring a wide-open urinary channel.
Understanding HoLEP: Why It is the Surgical Gold Standard
Unlike standard TURP which scrapes tissue layer by layer like peeling an apple from inside, HoLEP utilizes laser energy to find the true surgical capsule plane and enucleates the entire adenoma as intact anatomical lobes.
STEP 01
Capsular Enucleation
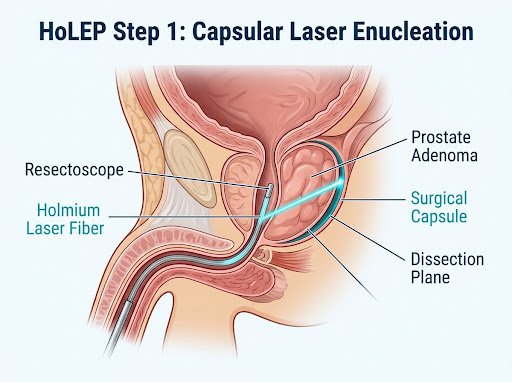
A 550µm Holmium laser fiber serves as an anatomical scalpel, dissecting the obstructing adenoma cleanly along the natural anatomical capsule plane without cutting through vascular tissue, pushing the freed lobes directly into the bladder.
STEP 2
Intravesical Morcellation
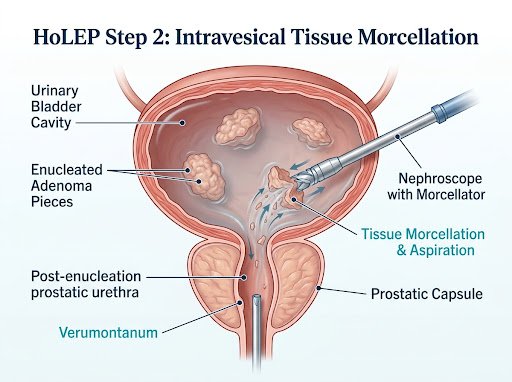
The enucleated prostate lobes resting inside the bladder are captured by an integrated high-speed tissue morcellator. Tissue fragments are aspirated safely out of the body and sent for 100% complete histological analysis to rule out malignancy.
STEP 03
Restored Open Lumen
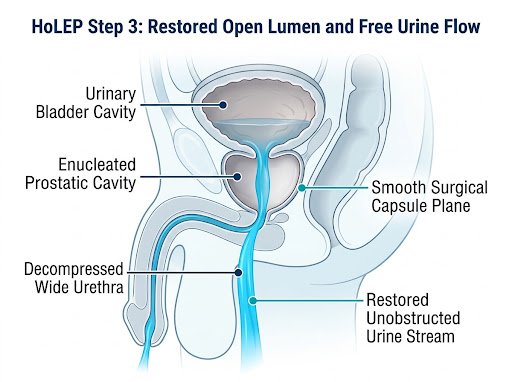
With the entire obstruction removed down to the capsular boundary, an expansive urinary channel is recreated. Bladder detrusor muscle work is instantly halved, offering permanent symptomatic relief with less than 1% lifetime reoperation risk.
Clinical Comparison: HoLEP vs. Traditional TURP vs. Robotic Simple Prostatectomy
Review comparative clinical parameters established by international urology guidelines (AUA / EAU).
Clinical Criteria
HoLEP (Holmium Laser)
Traditional TURP
Robotic Simple Prostatectomy
Eligible Prostate Size
Any size (30g to 250g+) size-independent
Limited to <60 - 80g safely
Best for >100g, but requires abdomen entry
External Cuts / Incisions
Zero incisions (100% endoscopic)
Zero incisions (endoscopic)
4 to 5 abdominal puncture ports
Blood Loss & Coagulation
Virtually bloodless; safe on blood thinners
Higher risk of bleeding; requires stop of thinners
Minimal blood loss
Catheter Duration
12 to 24 hours typical
2 to 4 days
5 to 7 days
Hospital Stay
24 to 48 hours discharge
3 to 5 days
2 to 3 days
Long-Term Reoperation Rate
< 1% at 10-20 years (Definitive)
10% to 15% due to adenoma regrowth
< 2% at 10 years
Tissue Retrieved for Biopsy
100% morcellated tissue sent for histology
Partial tissue; charring artifacts
100% specimen removed
Who is an Ideal Candidate for HoLEP?
HoLEP is endorsed globally when standard medical therapy or conventional resections are either high risk or ineffective.
Large or Giant Prostate (>80g - 250g+)
Men who have been previously advised to undergo open surgery with substantial abdominal incisions. HoLEP removes even massive glands completely via natural urethral access.
Recurrent Retention & Catheter Dependence
Patients who have failed a Trial Without Catheter (TWOC), or have severe bladder over-distension and chronic urinary retention requiring recurring catheterization.
Patients on Blood Thinners (Anticoagulants)
Men with cardiac stents or history of stroke taking aspirin, clopidogrel, or warfarin who cannot safely pause medication. Holmium laser seals vessels instantaneously during enucleation.
Secondary Bladder Complications
Presence of large bladder stones (which can be lasered simultaneously during HoLEP), frequent recurrent UTIs, diverticula, or impending renal impairment from backpressure.
Failed Medical Therapy or Prior TURP
Men who no longer respond to Tamsulosin or Dutasteride, or who underwent a partial TURP 5-10 years ago and are now suffering from renewed adenomatous tissue regrowth.
Personalized Clinical Candidacy Assessment
Comprehensive clinical candidacy evaluation assesses gland volume (40g to 250g+), uroflowmetry Qmax rates, post-void residual urine, and serum PSA. Tailored for patients seeking a definitive, bloodless endoscopic alternative to open surgery or repeat TURP.
The 5-Step Clinical Care Journey at Rajshree Apollo
From precise pre-op diagnostic mapping to rapid discharge, experience structured surgical protocols designed for supreme comfort.
01 / DIAGNOSIS
Multiparametric Evaluation
Detailed uroflowmetry (Qmax flow speed), post-void residual ultrasound, serum PSA, and serum creatinine to ensure complete urinary safety.
02 / SURGERY
Laser Enucleation
Performed under spinal anesthesia using a dedicated high-power Holmium 100W laser. Saline irrigation eliminates any risk of TURP syndrome.
03 / CLEARANCE
Tissue Morcellation
Enucleated lobes in the bladder are gently fragmented and suctioned out, ensuring 100% of the tissue is preserved for pathology screening.
04 / RECOVERY
Day 1-2 Catheter Removal
Catheter is typically removed within 18 to 24 hours. Patients undergo a supervised voiding trial before walking comfortably home.
05 / DURABILITY
Lifelong Urinary Freedom
Restored stream with near-zero risk of re-operation at 10-20 years, supported by scheduled checkups at the Rajshree Apollo OPD desk.
Patient Clinical Education
Honest, transparent answers regarding HoLEP surgery, recovery, and long-term quality of life.
1. Will HoLEP affect sexual health and erectile function?
HoLEP does not damage the external cavernous nerves responsible for penile erection, as dissection stays strictly inside the prostate capsule. Most men experience unchanged or even improved erectile function after relieving severe urinary obstruction. Like all anatomical prostate surgeries, retrograde ejaculation (dry orgasm) is common, as the wide-open neck allows ejaculate to enter the bladder and exit safely during next voiding.
2. Why is HoLEP superior to conventional TURP for large prostates?
Traditional TURP is strictly time-limited (max 60 minutes) to avoid fluid absorption poisoning (TURP syndrome) and bleeding. In large glands (>80g), TURP only carves a partial tunnel, leaving residual tissue that regrows within 5 to 10 years. HoLEP removes the whole adenoma right to the capsular shell regardless of size, using sterile saline irrigation that eliminates TURP syndrome completely.
3. Can HoLEP be performed if I am on blood thinners for heart stents?
Yes. The Holmium laser operates at a 2140nm wavelength with extraordinary shallow tissue penetration (0.4mm), instantaneously coagulating blood vessels as the adenoma is enucleated. Under Dr. Chipde’s cardiac-synchronized surgical protocol at Rajshree Apollo, patients taking aspirin or clopidogrel can safely undergo HoLEP with minimal transfusion risk.
4. How long does the urinary catheter stay in place after HoLEP?
In the vast majority of our patients, the catheter is safely removed within 18 to 24 hours (next morning). After passing clear urine during a supervised trial void, patients are discharged home comfortably without any external bags or drainage tubes.
5. Will the prostate ever grow back after HoLEP surgery?
Because HoLEP strips away 100% of the transition zone adenoma down to the surgical capsule, recurrence is exceptionally rare. International studies following patients for over 20 years confirm a re-operation rate of less than 1%, making HoLEP the closest procedure to a permanent cure for benign prostatic hyperplasia.
Don't Endure Lifelong Catheters or Agonizing Urinary Blockage
Take advantage of modern, minimally invasive Holmium laser surgery at Central India’s leading laser urology hospital.
Visit Dr. Chipde at Rajshree Apollo Hospitals Indore
Conveniently accessible in Vijay Nagar, Indore. Book an express in-clinic consultation or connect on WhatsApp.
Rajshree Apollo Hospitals, Indore
- Practice Address:
Rajshree Apollo Hospitals, Sector-D, Scheme No. 74C, Vijay Nagar, Indore, Madhya Pradesh 452010
- OPD Clinic Hours:
Monday to Saturday: 10:00 AM – 06:00 PM (Sunday by emergency appointment)
- Direct Phone & WhatsApp: